
An Uninsured Patient Good Faith Estimate Letter is a mandatory document under the No Surprises Act, providing transparent pricing to self-pay individuals before medical services. This estimate ensures patients understand potential costs to prevent unexpected financial burdens and billing disputes. Establishing clear communication builds trust and ensures legal compliance for healthcare providers. Below are some ready to use templates.

Image cover: Good Faith Estimate Templates and Sample Letters for Uninsured Patients
Letter Samples List
- Initial Uninsured Patient Good Faith Estimate Letter
- Revised Uninsured Patient Good Faith Estimate Letter
- Self-Pay Patient Annual Good Faith Estimate Letter
- Primary Care Visit Good Faith Estimate Letter
- Diagnostic Imaging Uninsured Patient Good Faith Estimate Letter
- Outpatient Procedure Good Faith Estimate Letter
- Specialist Consultation Good Faith Estimate Letter
- Laboratory Services Good Faith Estimate Letter
- Recurring Treatment Good Faith Estimate Letter
- Urgent Care Walk-In Good Faith Estimate Letter
- Pediatric Wellness Exam Good Faith Estimate Letter
- Chronic Disease Management Good Faith Estimate Letter
- Good Faith Estimate Dispute Acknowledgment Letter
- Good Faith Estimate Patient Signature Confirmation Letter
Initial Uninsured Patient Good Faith Estimate Letter
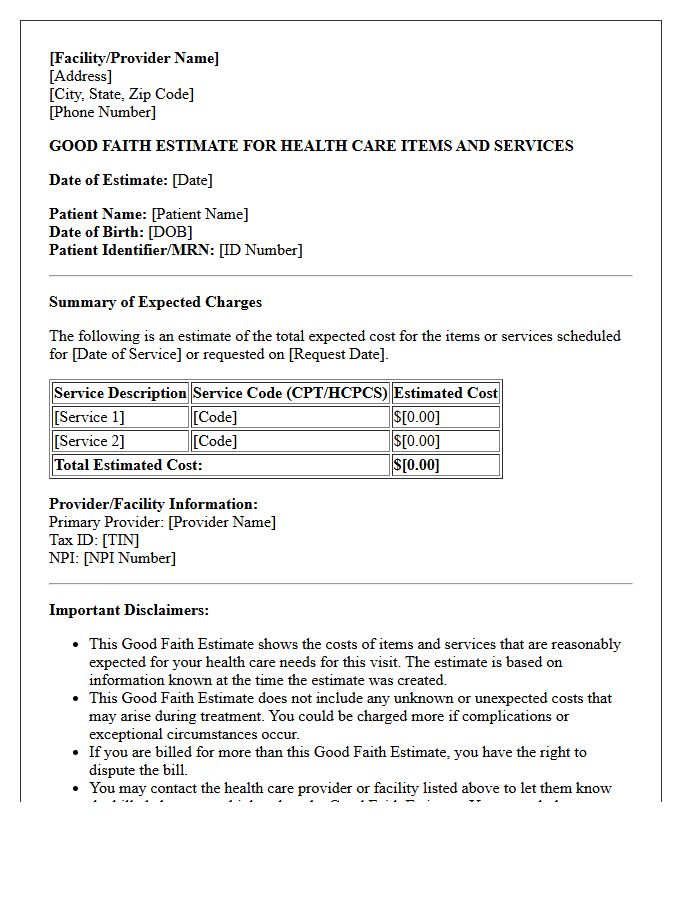
Under the No Surprises Act, providers must give a Good Faith Estimate to uninsured or self-pay patients. This letter outlines expected charges for scheduled medical services or upon request. It ensures transparency, helping patients understand potential costs before receiving care. If the final bill exceeds the estimate by $400 or more, the patient has the legal right to dispute the charges through a federal process. This document is a critical consumer protection tool designed to prevent unexpected financial burdens in healthcare.
Revised Uninsured Patient Good Faith Estimate Letter
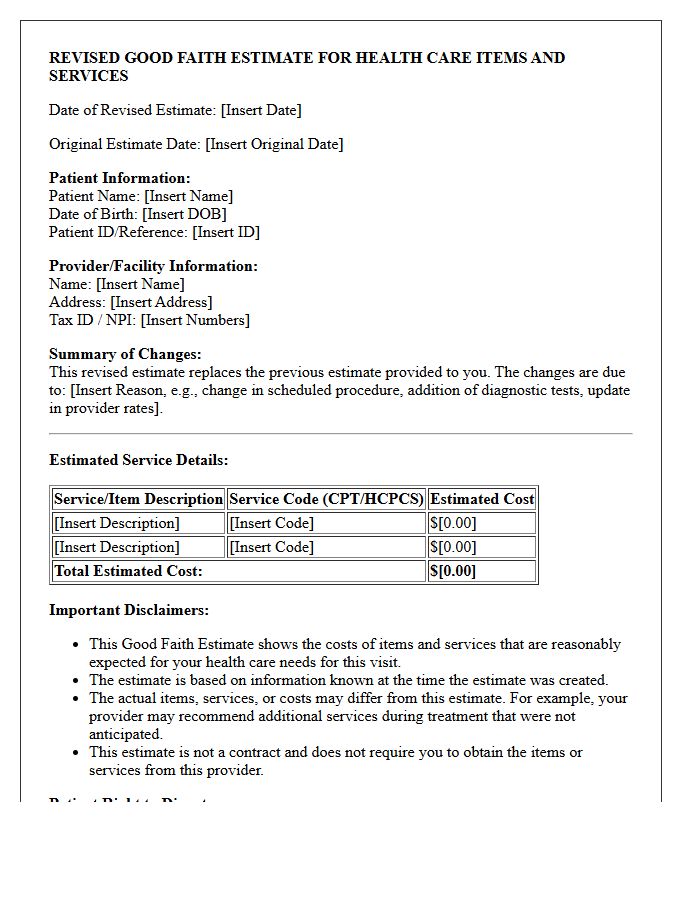
The Revised Uninsured Patient Good Faith Estimate Letter is a critical regulatory document mandated by the No Surprises Act. It provides self-pay and uninsured individuals with a clear cost projection for scheduled medical services. Providers must issue these estimates to prevent unexpected financial burdens, ensuring transparency before treatment. Key updates focus on standardized formatting and the inclusion of comprehensive diagnostic codes. If the final bill exceeds the estimate by $400 or more, patients gain the legal right to initiate the Patient-Provider Dispute Resolution process to challenge the charges.
Self-Pay Patient Annual Good Faith Estimate Letter

Under the No Surprises Act, healthcare providers must give self-pay or uninsured patients a Good Faith Estimate (GFE) before scheduled services. This document outlines the total expected costs for items and services, helping patients avoid unexpected medical bills. It is important to request an annual update to reflect current pricing and treatment plans. If the final charges exceed the estimate by $400 or more, you have the right to initiate a patient-provider dispute resolution process to challenge the billing discrepancy and protect your financial rights.
Primary Care Visit Good Faith Estimate Letter

A Primary Care Visit Good Faith Estimate is a document required by the No Surprises Act for uninsured or self-pay patients. It provides a transparent, written notification of the expected costs for scheduled medical services before treatment occurs. This letter helps patients avoid unexpected billing by detailing professional fees and diagnostic tests. If the final charges exceed this estimate by $400 or more, you have the legal right to dispute the bill. Always keep this document as a reference for your financial responsibility and healthcare rights.
Diagnostic Imaging Uninsured Patient Good Faith Estimate Letter
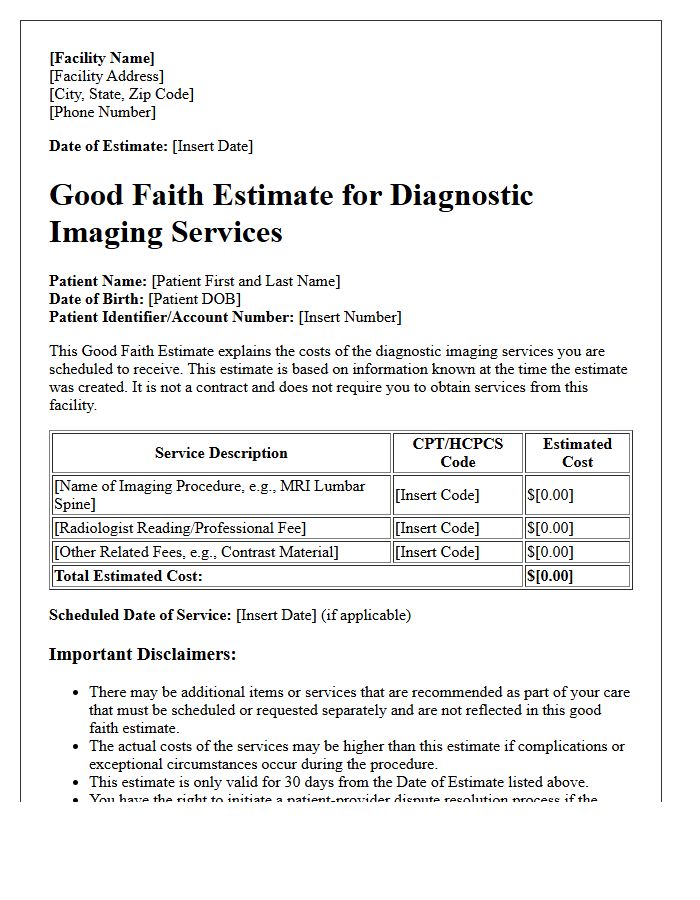
Under the No Surprises Act, healthcare providers must give a Good Faith Estimate to uninsured or self-pay patients before diagnostic imaging. This letter provides a transparent cost projection for scheduled services, helping patients avoid unexpected medical bills. It must include a detailed breakdown of expected charges and is legally binding within a $400 threshold. If the final bill significantly exceeds this estimate, patients have the right to initiate a provider-patient dispute resolution process. Always request this document in writing to ensure financial protection and informed healthcare decision-making.
Outpatient Procedure Good Faith Estimate Letter
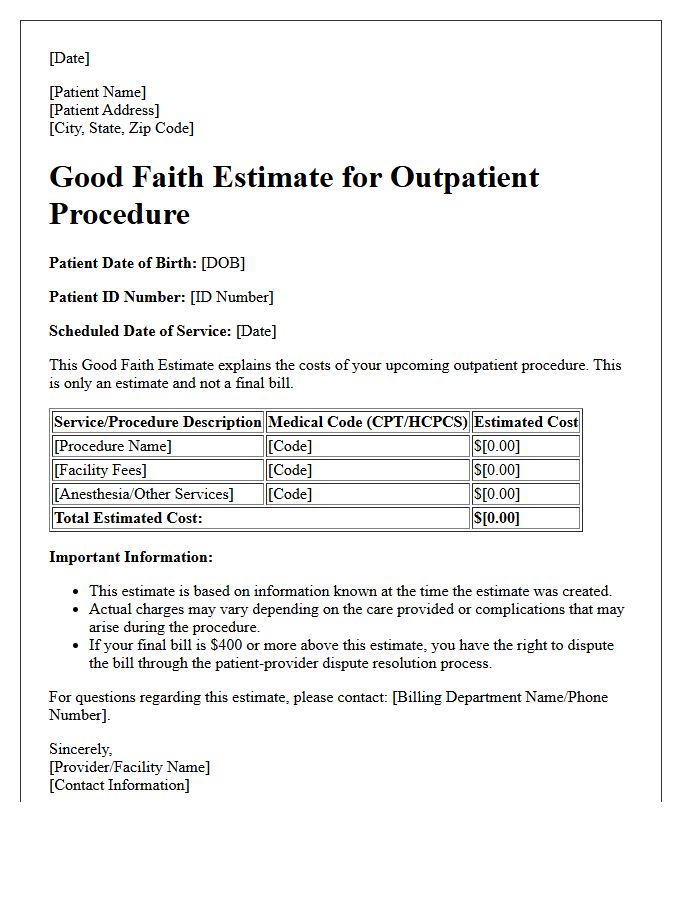
An Outpatient Procedure Good Faith Estimate is a mandatory written document provided to uninsured or self-pay patients before scheduled medical services. Under the No Surprises Act, this financial disclosure outlines the expected costs for items and services reasonably anticipated for your healthcare visit. It helps prevent unexpected billing by providing price transparency in advance. If the final bill exceeds the estimate by $400 or more, you have the legal right to dispute the charges through a patient-provider dispute resolution process. Always keep this letter for your records to ensure billing accuracy.
Specialist Consultation Good Faith Estimate Letter
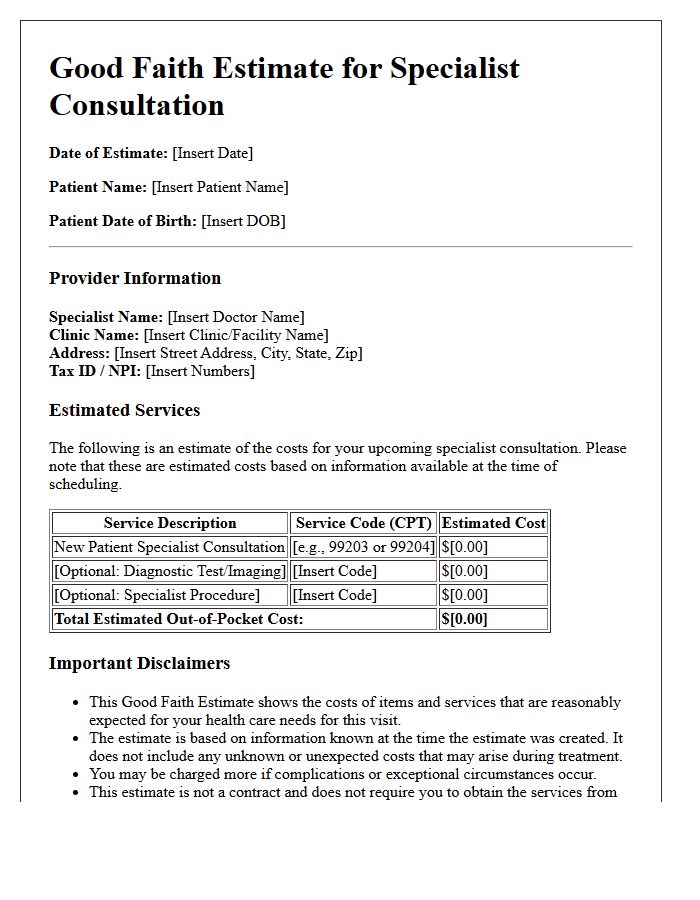
A Specialist Consultation Good Faith Estimate Letter is a mandatory document under the No Surprises Act. It provides uninsured or self-pay patients with a transparent cost breakdown before a scheduled appointment. This estimate includes expected charges for the consultation, diagnostic tests, and related professional fees. Receiving this letter helps you understand your financial responsibility upfront, preventing unexpected medical billing. If the final charges exceed the estimate by $400 or more, you have the legal right to initiate a patient-provider dispute resolution process to contest the excess costs.
Laboratory Services Good Faith Estimate Letter

A Laboratory Services Good Faith Estimate (GFE) is a document providing uninsured or self-pay patients with an itemized breakdown of expected costs before medical tests occur. Mandated by the No Surprises Act, this letter ensures price transparency by listing potential laboratory fees and associated charges. Patients should receive this estimate in writing at least one business day before a scheduled appointment. If the final bill exceeds the estimate by $400 or more, you have the legal right to dispute the charges through the federal patient-provider dispute resolution process.
Recurring Treatment Good Faith Estimate Letter

Under the No Surprises Act, a Good Faith Estimate provides uninsured or self-pay patients with a clear breakdown of expected costs before receiving care. For recurring treatments, such as therapy or chronic care, providers must issue a single estimate covering the frequency and total projected expense for up to twelve months. This document protects you from unexpected medical bills, ensuring financial transparency. If the final charges exceed the estimate by $400 or more, you have the legal right to initiate a patient-provider dispute resolution process to challenge the billing discrepancy.
Urgent Care Walk-In Good Faith Estimate Letter
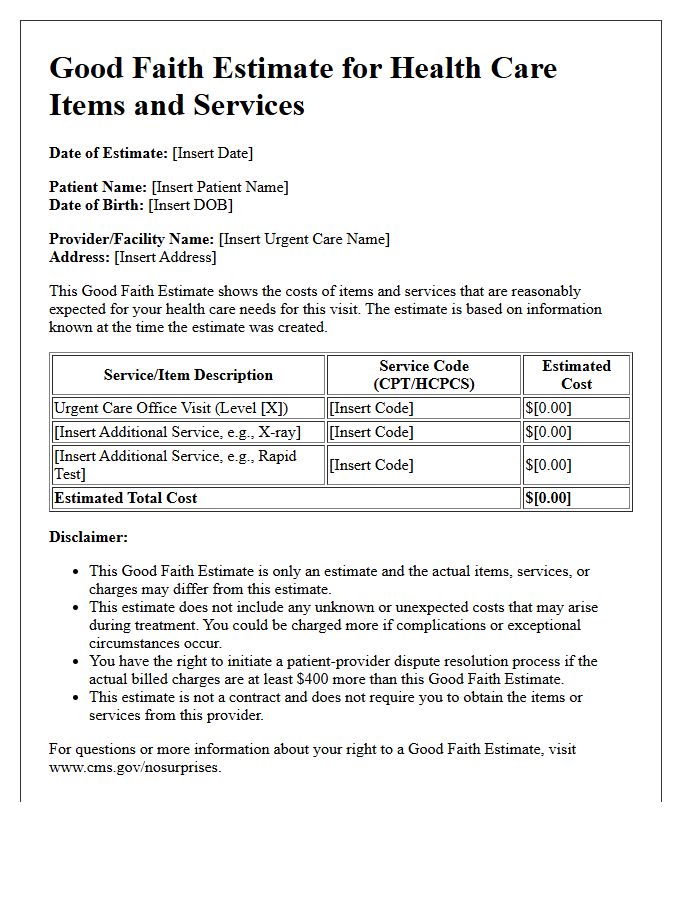
An Urgent Care Good Faith Estimate is a mandatory document provided to uninsured or self-pay patients before receiving medical services. Under the No Surprises Act, this letter outlines the expected costs for your visit, including diagnostic tests and procedures. It serves as a financial protection tool, ensuring transparency and preventing hidden billing. If your final bill exceeds the estimate by $400 or more, you have the legal right to dispute the charges. Always request this written estimate during check-in to manage your healthcare expenses effectively.
Pediatric Wellness Exam Good Faith Estimate Letter
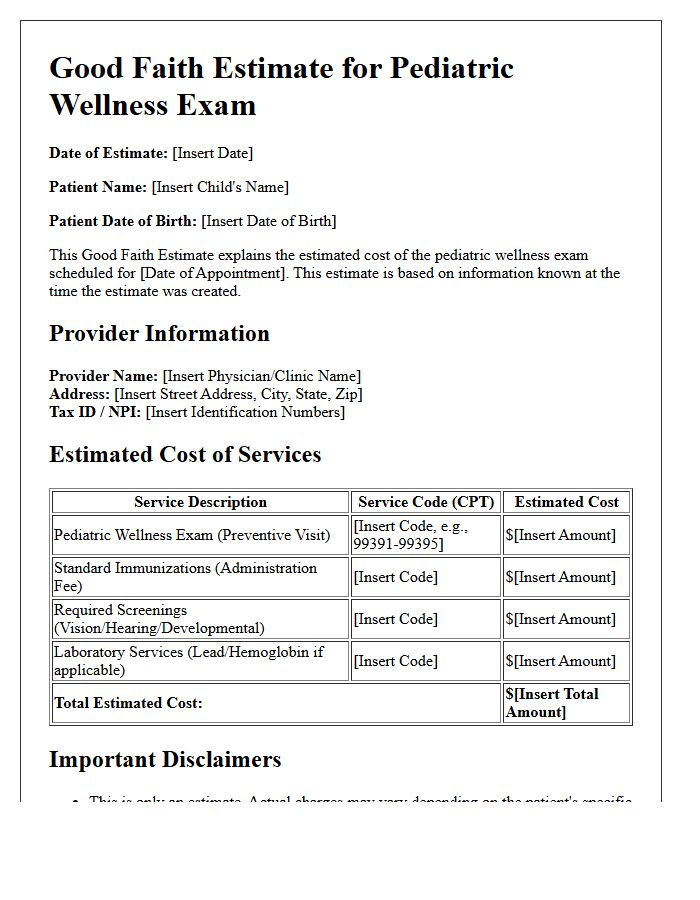
A Good Faith Estimate for a pediatric wellness exam is a transparent document outlining the projected costs for uninsured or self-pay patients. Mandated by the No Surprises Act, this letter provides an itemized list of expected charges, including physical assessments and immunizations, before the appointment. It ensures families avoid unexpected financial burdens by establishing clear pricing upfront. If the final bill exceeds the estimate by $400 or more, parents have the legal right to dispute the charges through a formal resolution process.
Chronic Disease Management Good Faith Estimate Letter
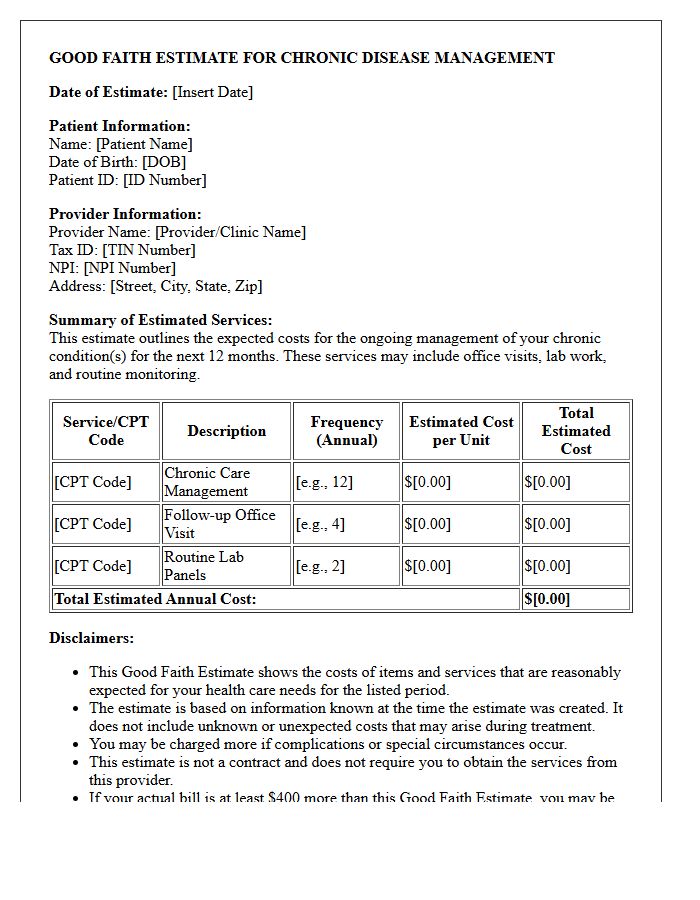
A Good Faith Estimate (GFE) for chronic disease management is a federally mandated document outlining the projected costs of your long-term medical care. Under the No Surprises Act, healthcare providers must give uninsured or self-pay patients a clear breakdown of expected charges before scheduled appointments. This transparency helps you anticipate expenses for recurring visits, labs, and therapies. Reviewing your GFE allows you to compare prices and protects you from unexpected billing discrepancies, ensuring you can effectively budget for your ongoing healthcare journey without financial surprises.
Good Faith Estimate Dispute Acknowledgment Letter

A Good Faith Estimate Dispute Acknowledgment Letter is a formal notice sent by a Selected Dispute Resolution entity to confirm they have received your request to challenge a medical bill. It signifies the start of the Patient-Provider Dispute Resolution process under the No Surprises Act. This document is essential because it verifies that your case is under review, providing a case tracking number and pausing collection efforts. This ensures you are not required to pay the disputed amount while the billing discrepancy is being officially investigated for accuracy.
Good Faith Estimate Patient Signature Confirmation Letter

A Good Faith Estimate Patient Signature Confirmation Letter serves as formal documentation that a healthcare provider informed an uninsured or self-pay patient about anticipated costs. This document ensures compliance with the No Surprises Act by verifying the patient received and acknowledged their financial estimate before treatment. It protects both parties by establishing transparent communication regarding expected medical fees. Obtaining this signed acknowledgment is a critical step in the billing process to prevent future disputes and maintain legal regulatory standards in medical practices.
What is a Good Faith Estimate for uninsured patients?
A Good Faith Estimate (GFE) is a document provided by healthcare providers that outlines the total expected costs for scheduled items or services. Under the No Surprises Act, providers must give this written estimate to patients who are uninsured or self-pay at least one to three business days before a scheduled procedure.
Who is eligible to receive a Good Faith Estimate letter?
Any individual who does not have health insurance or who chooses not to use their insurance (self-pay) to cover a medical service is entitled to receive a Good Faith Estimate. This applies to all non-emergency healthcare services provided by hospitals, clinics, and individual practitioners.
What information must be included in a Good Faith Estimate?
The letter must include a detailed list of expected services, the associated diagnosis and billing codes, and the estimated costs for each. It should also include the provider's contact information, a disclaimer that the final bill may vary, and instructions on how to dispute the bill if the actual charges significantly exceed the estimate.
What should I do if my final medical bill is higher than the estimate?
If the final charges are $400 or more above the total amount listed in your Good Faith Estimate, you have the right to initiate the Patient-Provider Dispute Resolution process. You must file a dispute claim within 120 calendar days of receiving the final bill to challenge the excess charges.
When should a provider deliver the Good Faith Estimate letter?
If you schedule a service at least three business days in advance, the provider must give you the estimate within one business day of scheduling. If the service is scheduled ten or more business days in advance, the estimate must be provided within three business days. You can also request an estimate before scheduling any appointment.


Comments